Mouth Taping for Snoring: What the Research Says
No — mouth taping does not stop snoring, according to the best review we have. A 2025 review of 10 studies found only 2 showed any statistically significant improvement, and it rated every study poor quality. The safety side is clearer: taping can be risky with a blocked nose or undiagnosed sleep apnea.
Applies to: anyone who saw a social-media video about mouth taping for snoring and wants the evidence before trying it.
Safety warning: who should never try mouth taping for snoring
The 2025 review's authors concluded, verbatim: "there is a potentially serious risk of harm for individuals indiscriminately practicing this trend." The specific danger is asphyxiation risk when the nose is blocked — tape over the mouth removes your only open airway while you sleep. Four of the ten studies in the review warned of asphyxiation risk if the nose is blocked or if regurgitation occurs.
Do not tape your mouth if: you have a cold, allergies, congestion, a deviated septum, or any trouble breathing through your nose · you snore loudly with gasping, choking, or breathing pauses (possible sleep apnea) · you have asthma, COPD, or another breathing condition · you have reflux or anything that makes vomiting in your sleep likely · you are a child or care for one.
This page is education, not medical advice. Talk to a qualified clinician about snoring that includes breathing pauses — it needs evaluation, not tape. (Rhee et al., 2025)
If a social-media video told you to try mouth taping for snoring, read this first. A 2025 review of 10 studies found only 2 showed any statistically significant improvement, and the review authors warned the trend carries a potentially serious risk of harm. Below: exactly what the ten studies tested, why the two positive ones don't prove the trend, and what to ask instead.
So, does mouth taping work for snoring? For the general snorer, the honest answer is no. The only wins in the literature are two tiny pilots in carefully selected mild-apnea mouth-breathers — people screened to have clear noses, measured for one week or less, with no control group. Nothing in the research supports taping as a snoring remedy for ordinary snorers, and nothing supports it as a treatment for sleep apnea: the authors of the best-known pilot wrote that taping is not recommended for moderate or severe apnea because it may impose dangers rather than benefits. The review's verdict is negative overall, with a real harm warning attached — and that is the verdict this page follows.

What the 2025 review found
The best evidence on mouth taping is a systematic review published in PLOS ONE in 2025 by Rhee and colleagues. It followed PRISMA guidelines, used a librarian-designed search of MEDLINE, Embase and Google Scholar from February 1999 to February 2024, and was registered with PROSPERO under identifier CRD42024509650 (Rhee et al., 2025). The search found 120 articles; after 34 duplicates were removed, 86 were screened, 62 were excluded, 24 went to full-text review, and 10 met the inclusion criteria (Rhee et al., 2025).
The result, in the abstract's own words: "Two studies showed statistically significant improvement in established markers of sleep apnea such as apnea-hypopnea index (AHI) or oxygen desaturations. Other studies showed that mouth taping offered no differences and even discussed potential risks including asphyxiation in the presence of nasal obstruction. Many studies excluded anyone with nasal obstruction or pathology." The conclusion: "Based on the data presented by these 10 different studies, it seems that there is a potentially serious risk of harm for individuals indiscriminately practicing this trend. Further studies are required to elucidate any clinical benefit this practice may have." (Rhee et al., 2025)
The ten studies were small and uneven: six prospective cross-sectional studies, one randomised controlled trial, one prospective cohort study, one retrospective cohort study, and one prospective crossover study. Sample sizes ranged from 9 to 71 participants. Eight of the ten used adhesive tape or a sealing device to close the mouth; two used a chin strap. The participants' mean or median ages ranged from 38 to 64 years, body mass index from 24 to 35, and baseline AHI from 13 to 47 events per hour — that is, most of the people studied already had sleep apnea, not simple snoring (Rhee et al., 2025). Only two of the ten studies included patients with mild apnea (AHI under 15), and four excluded anyone with any form of nasal obstruction (Rhee et al., 2025).
One discrepancy in the review itself, flagged honestly because this site checks its sources: the abstract reports 213 patients in total across the ten studies, while the Results section reports 233 total patients. The two figures cannot both be right, and the paper does not explain the difference. This page follows the abstract's figure (213) and notes the mismatch here, so a reader who opens the paper is not surprised by it.
The two positive studies, in detail
Lee et al., 2022 — the tape study. Twenty mouth-breathers with mild obstructive sleep apnea, median age 38, median body mass index 24.5, 19 men and 1 woman, slept with 3M silicone hypoallergenic tape — a 4 cm strip across the philtrum — for one week, with home sleep tests before and after (Lee et al., 2022). The median apnea-hypopnea index fell from 8.3 to 4.7 events per hour, which the authors report as a 47% reduction (p=0.0002); the median snoring index fell from 303.8 to 121.1 events per hour, also reported as 47% (p=0.0002). The oxygen desaturation index fell from 8.7 to 5.8 (p=0.0003) and the lowest oxygen saturation rose from 82.5% to 87% (p=0.049). Thirteen of the twenty — 65% — were "responders", meaning their snoring index fell by at least half (Lee et al., 2022).
Read the fine print before the numbers impress you. The study was retrospective, with no control group and one week of follow-up. The participants were narrowly selected: ages 20 to 60, body mass index under 30, AHI under 15, witnessed mouth-breathing, and a dry throat on waking — and anyone whose tape came off by morning, who had significant retrognathia, tonsil hypertrophy, previous nose, palate or tongue surgery, or severe medical disease was excluded. People with nasal obstruction had it treated with medication and nasal spray first (Lee et al., 2022). And the authors themselves limited the claim: "Mouth-taping is not recommended for moderate or severe OSA patients because it may impose dangers rather than benefits in these patients." The 47% figures are the authors' own — the median of each patient's percentage change, as their Table 2 shows — not a ratio computed from the two medians.
Huang & Young, 2015 — the porous patch study. Thirty patients with mild sleep apnea (AHI 5 to 15) and habitual mouth-breathing wore a porous oral patch — three layers of silicone sheet, polyurethane foam and polyurethane film — and all thirty slept with their mouths closed while wearing it (Huang & Young, 2015). The median AHI fell from 12.0 to 7.8 events per hour (P<.01); the median snoring index fell from 146.7 to 40.0 events per hour (P<.01); snoring intensity fell from 49.1 to 41.1 decibels; daytime sleepiness on the Epworth scale fell from 8.1 to 5.2; and self-rated snoring fell from 7.5 to 2.4 on a ten-point scale (Huang & Young, 2015). It was a prospective pilot with no control group, and the review rated all ten of its included studies as poor quality. Two small pilots, both uncontrolled, both in mild apnea, both in people screened to have clear noses: that is the entire positive case for mouth taping.
The other eight studies
The remaining eight studies are the part the videos never mention. They tested mouth taping and chin straps in people with sleep apnea and mouth-breathing, and found no differences — or found risks. The review's summary is blunt: other studies "showed that mouth taping offered no differences and even discussed potential risks including asphyxiation in the presence of nasal obstruction" (Rhee et al., 2025). Four of the ten studies explicitly discussed asphyxiation risk from oral occlusion in the presence of nasal obstruction or regurgitation (Rhee et al., 2025).
Two of the eight used chin straps rather than tape, and two combined a mouth seal with another device — a mandibular advancement device in one, a chin strap plus a nasal spray in another — so not all eight tested tape alone. The studies' baseline AHI values ran from 13 to 47 events per hour, meaning most participants had moderate to severe apnea, a population in which taping was never shown to help and in which the Lee authors explicitly advise against it (Rhee et al., 2025). The review rated every included study as poor quality — so the negative verdict is not a strong verdict built on strong studies. It is a weak evidence base that leans negative, with a safety warning attached.
Why the positive results do not generalise
Three reasons, each sufficient on its own. First, selection: the two positive studies enrolled only people with mild apnea, clear noses, and no complicating conditions — a slice of snorers that excludes most people who snore. Second, design: neither study had a control group, neither was blinded, and follow-up was one week or less. Snoring varies night to night, and a before-and-after measurement with no control cannot separate a treatment effect from a good week. Third, size: 20 and 30 people. A 47% median reduction in 20 people is a signal worth a proper trial, not a basis for a trend — and no proper trial has followed in the years since.
The backfire: when closing the mouth makes airflow worse
The most important study for a would-be taper is not one of the ten in the review — it is a 2024 trial that tested mouth closure directly. Yang and colleagues enrolled 66 people with sleep apnea, excluded 12 for insufficient baseline airflow, and studied the remaining 54 during drug-induced sleep endoscopy, closing the mouth by pressing on the chin until the teeth met (Yang et al., 2024). Mouth closure increased total inspiratory flow by 27.8 percentage points overall. But the average hid a split: airflow improved in the 32 patients with moderate mouth-breathing, did not change meaningfully in the 10 with near-zero mouth-breathing, and got worse — by 1.9 litres per minute — in the heaviest mouth-breathers, people with severe obstruction behind the soft palate (Yang et al., 2024).
The mechanism is the point: mouth breathing can be a backup airway. When the nose and the velopharynx are blocked, the mouth is the route air still uses — and closing it removes the backup. The authors' conclusion is a warning against one-size-fits-all advice: "In patients who breathe primarily through their mouth during sleep and have velopharyngeal obstruction, airflow worsens with mouth closure. Hence, personalized approaches to treating mouth breathing should be considered." (Yang et al., 2024) Note what this study did not do: it used manual closure under sedation during an exam, not tape overnight — so it proves the physiology, not the outcome of taping. But the physiology is exactly what makes indiscriminate taping dangerous for the people who need their mouths most.
Numbers that get confused
Two percentages circulate about mouth taping, and they belong to two different studies. Lee et al. 2022 reported a 47% reduction in both AHI and snoring index — the authors' own figures, the median of each patient's percentage change, in 20 people with taped mouths (Lee et al., 2022). Chen et al. 2015 reported a 34.4% reduction in snoring index — again the authors' own figure — in 25 people using a head-positioning pillow, not tape at all (Chen et al., 2015). The median snoring index in Chen fell from 218.0 to 115.0 events per hour; dividing those two medians by hand gives a different figure, which is not the paper's figure and not a valid calculation — the 34.4% is the median of the per-patient changes, computed by the authors from individual data (Chen et al., 2015). An earlier version of this site printed the hand-computed figure on five pages; it was wrong, and it has been corrected everywhere. The rule this site now follows: never re-derive a paper's number by your own arithmetic when the paper states its own figure.
The same confusion appears in a third place: a search result for a mouth-taping roundup attributes a "close to 47 percent" AHI reduction to "Huang et al. 2022". There is no Huang et al. 2022 mouth-taping trial with that figure — the 47% belongs to Lee et al. 2022, and Huang & Young's 2015 patch study reported an AHI fall from 12.0 to 7.8 without a percentage (Huang & Young, 2015). Attribution matters as much as arithmetic.
Brain fog: the claim with no trial behind it
Mouth taping is also sold as a fix for brain fog, on the theory that nasal breathing improves cognition. No trial has tested mouth taping for brain fog — not one of the ten studies in the review, and no study anywhere else that the review found. The claim's only cited science is a 2016 brain study that does not support it, and a 2024 study that contradicts it.
Zelano and colleagues recorded intracranial EEG in patients with medically refractory epilepsy and found that natural breathing synchronises electrical activity in the piriform cortex, amygdala and hippocampus, with oscillatory power peaking during inspiration and dissipating when breathing was diverted from nose to mouth. Parallel behavioural experiments showed that breathing phase enhances fear discrimination and memory retrieval (Zelano et al., 2016). Read that carefully: breathing phase changed the timing of memory retrieval within the breathing cycle. It did not make anyone smarter, it did not train memory, and it did not involve tape, sleep, or brain fog.
The follow-up is clearer. Schaefer and colleagues ran a visual recognition memory task with stimuli phase-locked to inhalation or exhalation, in separate nose-breathing and mouth-breathing sessions, and found that neither breathing route nor breathing phase had a significant impact on recognition memory performance, with the data supporting the null hypothesis (Schaefer et al., 2024). So the chain the brain-fog claim needs — nasal breathing improves memory, therefore taping the mouth shut improves thinking — fails at its first link. There is no evidence that taping helps brain fog, and the evidence cited for it says something else.
The 4-question safety screener
Four yes/no questions on mouth taping for snoring, adapted from the studies' own screening logic. Any "wrong" answer routes to "do not tape" — because that's where the evidence routes you. This runs entirely in your browser: nothing is sent anywhere, and it works as a plain list if scripts are off.
🛡️ Safety-first screener: should this even be on the table?
Answer honestly. 0 of 4 answered
1. Can you breathe comfortably through your nose, mouth closed, for two full minutes right now?
2. Do you have a cold, allergies, congestion, a deviated septum, or one nostril that blocks lying down?
3. Has anyone seen you gasp, choke, or pause breathing in your sleep?
4. Do you have asthma, COPD, another breathing condition — or is this for a child?
What to try instead
The reason most people mouth-breathe at night is not mysterious: the nose is blocked, or the airway collapses in the supine position. Treat the reason, not the mouth. Clear congestion — treat allergies, clear a cold, and ask a clinician about a deviated septum or chronic nasal obstruction rather than taping over it. Sleep on your side: snoring and apnea are both worse on the back, and the Lee study itself found the worst AHI in the supine position (a median of 9.4 events per hour, against 3.2 when not supine) (Lee et al., 2022). Keep the bedroom air humid, which keeps nasal passages from drying and swelling shut overnight.
If snoring comes with gasping, choking, breathing pauses, morning headaches, or daytime sleepiness, that is not a taping question — it is a sleep evaluation question. Continuous positive airway pressure is the treatment of choice for obstructive sleep apnea (Lee et al., 2022), and it is prescribed after testing, not after a video. A sleep study — in a lab or at home — is the step the trend skips, and it is the step that matters most: it distinguishes simple snoring from apnea, and apnea from something else entirely.
What the evidence cannot tell you
The evidence base is small and entirely poor quality by the review's own rating. The ten studies span 1999 to 2024, with sample sizes from 9 to 71, and only one was a randomised controlled trial (Rhee et al., 2025). No study tested taping in ordinary snorers without apnea, none followed anyone longer than a few weeks, and none tested taping for brain fog, CPAP mask leak, or sleep quality as a primary outcome.
Key takeaways
- A 2025 systematic review of 10 studies found no benefit in 8; the 2 positive studies were tiny, uncontrolled pilots in selected mild-apnea mouth-breathers (Rhee et al., 2025).
- The review's authors warned of "a potentially serious risk of harm" for indiscriminate taping, including asphyxiation with a blocked nose.
- Lee et al. 2022 (n=20): median AHI 8.3 → 4.7 and snoring index 303.8 → 121.1, both reported as 47% by the authors — and the authors advise against taping for moderate or severe apnea.
- Huang & Young 2015 (n=30): median AHI 12.0 → 7.8 and snoring index 146.7 → 40.0 with a porous patch — uncontrolled, poor quality.
- Yang et al. 2024 (n=54): closing the mouth worsened airflow in the heaviest mouth-breathers — the mouth can be a backup airway.
- Chen et al. 2015 reported 34.4%, not the hand-computed figure that circulated before — dividing two medians is not a valid calculation, and the re-derived number is an error.
- No trial has tested mouth taping for brain fog; the cited brain studies do not support the claim.
- Never tape with a blocked nose, suspected apnea, a breathing condition, reflux, or for a child — and get snoring with breathing pauses evaluated, not taped.
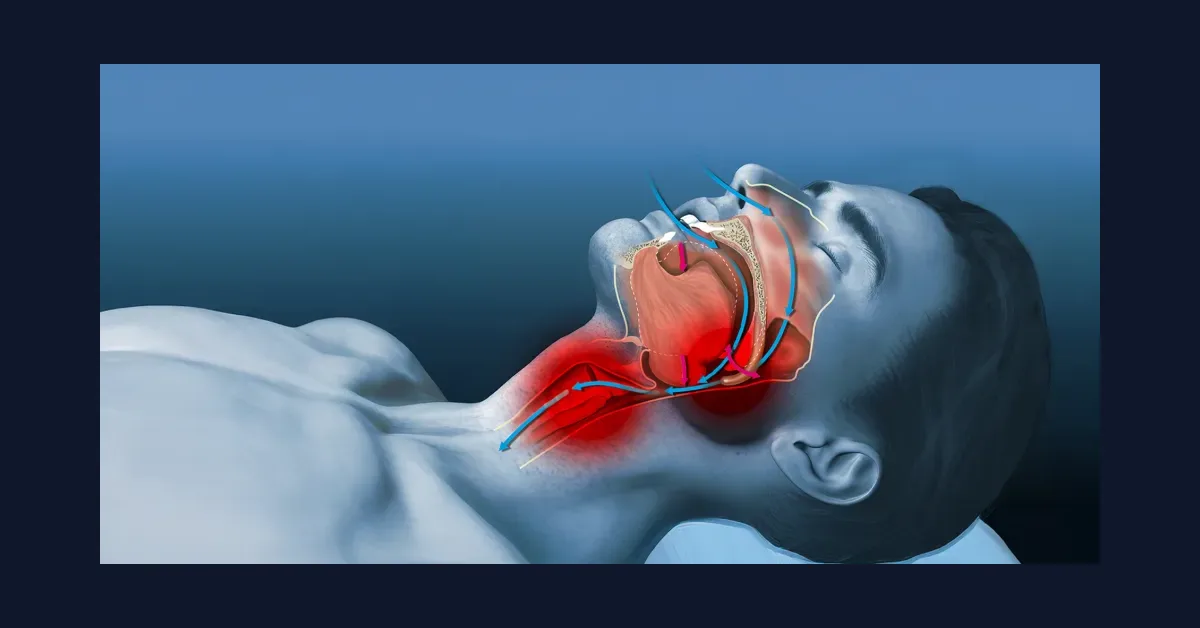
Questions people actually ask
Does mouth taping help snoring?
Is mouth taping safe?
Can mouth taping treat sleep apnea?
Can mouth taping make snoring worse?
Does mouth taping help brain fog?
How can I keep my mouth closed while sleeping without tape?
What type of tape should I use for mouth taping?
Does mouth taping help with CPAP mask leak?
References
- Rhee, J., Iansavitchene, A., Mannala, S., Graham, M. E., & Rotenberg, B. (2025). Breaking social media fads and uncovering the safety and efficacy of mouth taping in patients with mouth breathing. PLOS ONE, 20(5), e0323643. PMC12094774 / PubMed: 40397877
- Lee, Y. C., et al. (2022). Preliminary study of mouth taping in mouth breathers with mild obstructive sleep apnea. Healthcare, 10(9), 1755. PMC9498537 / PubMed: 36141367
- Huang, T. W., & Young, T. H. (2015). Novel porous oral patches for patients with mild obstructive sleep apnea and mouth breathing. Otolaryngology–Head and Neck Surgery, 152(2), 369–373. PubMed: 25450408 / DOI: 10.1177/0194599814559383
- Yang, H., et al. (2024). Mouth closure and airflow in patients with obstructive sleep apnea: a nonrandomized clinical trial. JAMA Otolaryngology–Head & Neck Surgery, 150(11), 1012–1019. PubMed: 39361293 / PMC12316187
- Zelano, C., et al. (2016). Nasal respiration entrains human limbic oscillations and modulates cognitive function. Journal of Neuroscience, 36(49), 12448–12467. PubMed: 27927961 / PMC5148230
- Schaefer, M., Hrysanidis, C., Lundström, J. N., & Arshamian, A. (2024). Phase-locked breathing does not affect episodic visual recognition memory but does shape its corresponding ERPs. Psychophysiology, 61(4), e14493. DOI: 10.1111/psyp.14493
- Chen, W. C., et al. (2015). Treatment of snoring with positional therapy in patients with positional obstructive sleep apnea syndrome. Scientific Reports, 5, 18188. PMC4676069 / PubMed: 26657174 — cited only as a contrast: a head-positioning pillow study, not a mouth-taping study; the authors' figure is 34.4%.
Last updated: 2026-11-21 by Adeel Farooq
Updated 21 November 2026 — full rewrite: key takeaways added; Rhee et al. 2025 patient-count discrepancy (abstract 213, Results 233) footnoted; Yang et al. 2024 backfire evidence added; brain-fog section rewritten from the primary studies; figure caption corrected.
How we researched this page
We mapped the reader questions for this page, then traced every number to its primary source, read first-hand on PubMed or PubMed Central: the Rhee et al. 2025 systematic review (PMID 40397877), the Lee et al. 2022 pilot (PMID 36141367, full text read), the Huang & Young 2015 pilot (PMID 25450408), the Yang et al. 2024 trial (PMID 39361293), the Zelano et al. 2016 brain study (PMID 27927961), the Schaefer et al. 2024 memory study (DOI 10.1111/psyp.14493), and the Chen et al. 2015 positional-therapy study (PMID 26657174, cited only as a contrast). No percentage on this page is re-derived by our own arithmetic: every figure is the paper's own stated figure. No manufacturer claims were used as evidence. Full method: how we research.